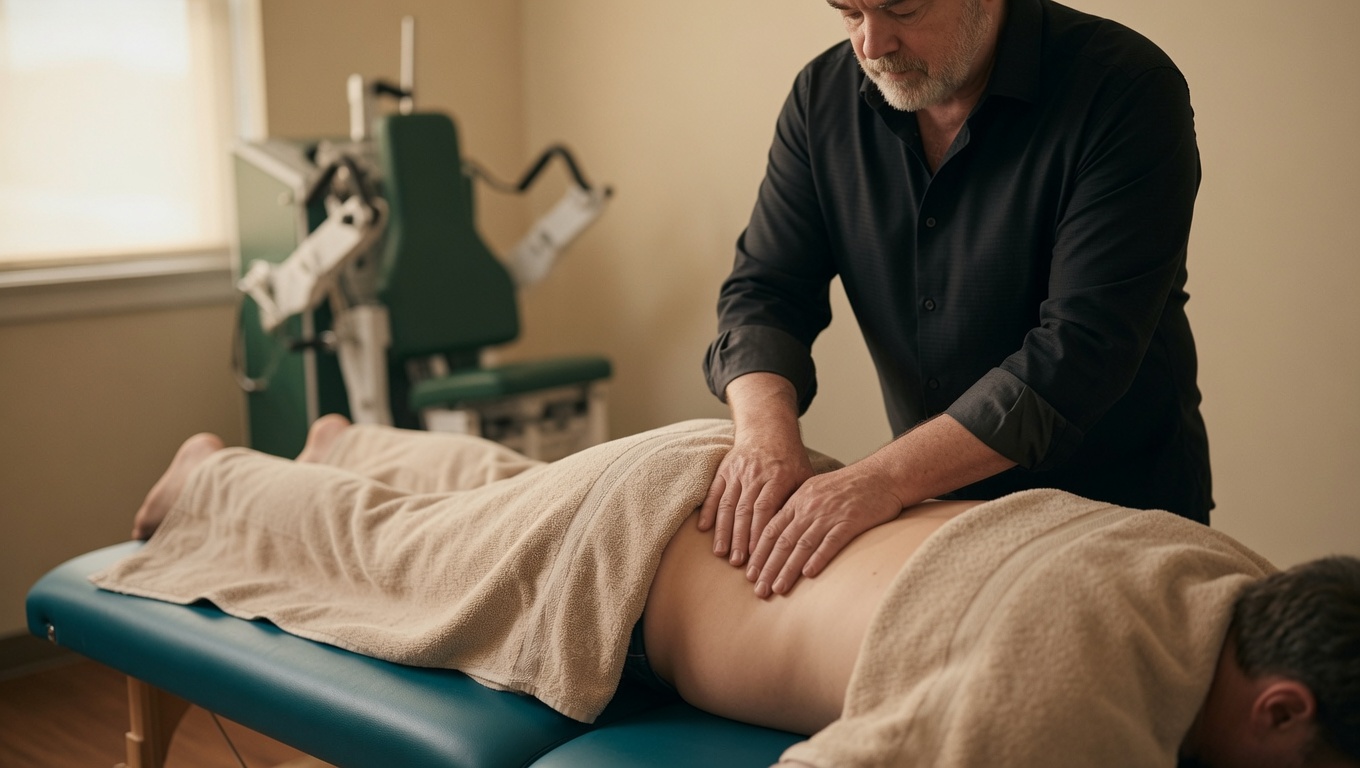

A client came in last month after two months on a MedX program at another facility. He had followed the protocol exactly, showed up for every session, and still felt like his lower back was "fighting" the machine. He was not wrong. Nobody had addressed the guarded, restricted tissue around his lumbar spine before asking that tissue to load against resistance. The machine was not the problem. The sequence was.
The Misconception: More Machine Time Equals Faster Results
Most people assume that if MedX spinal strengthening works, then doing more of it, sooner, will work better. That assumption skips a mechanical fact. A muscle that is locked in a protective guarding pattern, wrapped in adhered fascia, or compensating for a restricted joint above or below it does not strengthen cleanly. It strengthens around the dysfunction. You end up reinforcing the compensation instead of correcting it.
Isolated lumbar extension testing and training, the foundation of the MedX protocol, depends on the spine moving through its available range without the surrounding musculature bracing, twisting, or substituting. Graves' 1994 research on pelvic stabilization showed that isolated lumbar strength improved only when the pelvis was properly stabilized during testing and training, with strength gains of 23.5% in the stabilized group compared to a 1.2% decline in the unstabilized group. That is not a small technical detail. It means the position and quality of the surrounding tissue determines whether the strengthening stimulus reaches the target muscle at all.
What Manual Therapy Actually Prepares
Manual and muscular therapy is not a warm-up or a courtesy pass before the "real" treatment. It is a mechanical prerequisite. Restricted paraspinal tissue, adhered fascia, and guarded musculature change how force travels through the lumbar spine. If those restrictions are still present when a client sits into a MedX unit, the machine is measuring and training a compromised movement pattern. Understanding the psoas muscle and chronic low back pain helps explain why: a guarded, restricted muscle pulling on the lumbar spine changes the mechanics of everything downstream of it. The client burns effort. The muscle does not receive an honest load.
This is also where San Juan's 2005 EMG research becomes relevant to sequencing. Multifidus activation was 51% greater with pelvic stabilization in place. The multifidus is a deep stabilizer that responds to positioning and tissue quality before it responds to resistance. Manual therapy work aimed at restoring normal tissue mobility around the lumbar spine sets the stage for that stabilizer to actually participate once loading begins. Skip that step, and the deep stabilizers stay quiet while the larger, more superficial muscles compensate.
Why Sequencing Is Not Optional, It Is Structural
Think of it as a two-part mechanical process, not two separate treatments happening to coexist on a schedule. First, manual and muscular therapy addresses the soft tissue restrictions and guarding patterns that prevent normal movement. Second, MedX spinal strengthening loads the spine through a full, measured range once that movement is available. Reverse the order and the strengthening phase inherits every restriction that was never resolved.
This is not theoretical. Pollock's 1989 research demonstrated a 102% increase in lumbar extensor strength at 0 degrees over 10 weeks, training once per week, in healthy subjects without preexisting restrictions. That study was not measuring people working around adhered tissue or a guarded pattern. The strength gain reflects what is possible when the muscle is free to load properly from the start. Clients arriving with chronic guarding or restriction do not get that same clean stimulus until the restriction is addressed first.
35 years of hands-on clinical experience.
Ready to work on your problem. Call us and describe what you're dealing with.
Call 425-758-4619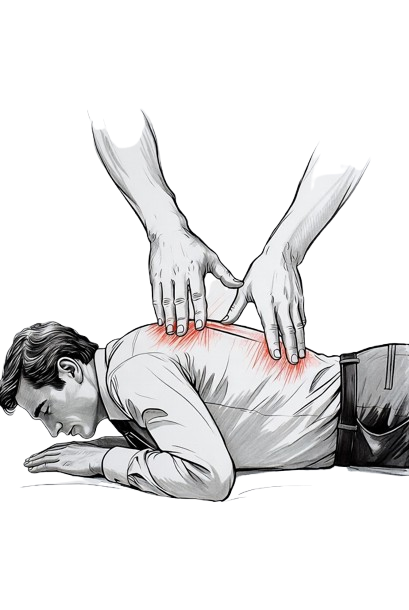
What This Looks Like With a Chronic Case
The client from the opening had spent two months training a compensation pattern. Once manual and muscular therapy work loosened the restricted tissue around his lumbar spine, and traction or decompression created space where segments had been compressed, the MedX sessions changed. Not because the machine changed. Because the tissue receiving the load finally could respond honestly.
This sequencing question matters even more for clients evaluating surgery. Nelson's 1995 study followed 627 completers of 895 chronic low back pain patients and found 76% excellent or good outcomes, with 94% of those good or excellent outcomes maintained at one year. Those are strong numbers, but they describe a full rehabilitation process, not an isolated machine protocol applied to unprepared tissue. In my own practice, of clients who arrived with spinal surgery already scheduled, 86.5% avoided surgery. That outcome depended on treating the whole mechanical picture in the correct order, not on any single modality alone, which is part of why MedX spinal strengthening works when everything else has failed only after the tissue is prepared to receive the load.
The Hard Truth About Skipping Steps
Sequencing is unglamorous. It does not make for a dramatic before-and-after story about one machine solving a spine. But a strengthening program built on top of unresolved tissue restriction is not a shortcut. It is a longer road disguised as a faster one. The muscle you are trying to strengthen cannot tell the difference between real capacity and compensation until you stop asking it to hide the difference.
You don't have to live with this. Backs and necks can get stronger, pain can ease, and the body is more capable of recovery than most people are told. This blog is here to give you honest, practical information about what actually helps. As we learn more, we'll keep sharing what works. If something here spoke to you, that's a good reason to reach out and start the first conversation.
Trent Shuford, LMT, Cert. MedX Tech.
